Your client has had Original Medicare and a Medigap plan for six years, and you’ve told her, truthfully, that Original Medicare doesn’t make her jump through prior authorization hoops the way a Medicare Advantage plan might. Then she calls, confused, because her doctor’s office in Columbus just told her a nerve stimulator procedure needs something called a “WISeR” review first, and she’s never heard the term and neither, maybe, have you. The WISeR model is real, it’s active right now in six states, and it’s the first time CMS has bolted AI-assisted prior authorization onto traditional fee-for-service Medicare at any real scale. This article covers what it actually requires, which states and services it touches today, what it costs when nobody explains it, the manual steps to find out if a specific client is affected, and where Ambrose’s War Room can take the research work off your plate.
Key takeaways
- The Wasteful and Inappropriate Service Reduction (WISeR) model adds AI-assisted prior authorization to a short list of services in Original Medicare, in Arizona, New Jersey, Ohio, Oklahoma, Texas, and Washington, from January 1, 2026 through December 31, 2031 (CMS, WISeR Model Provider Factsheet).
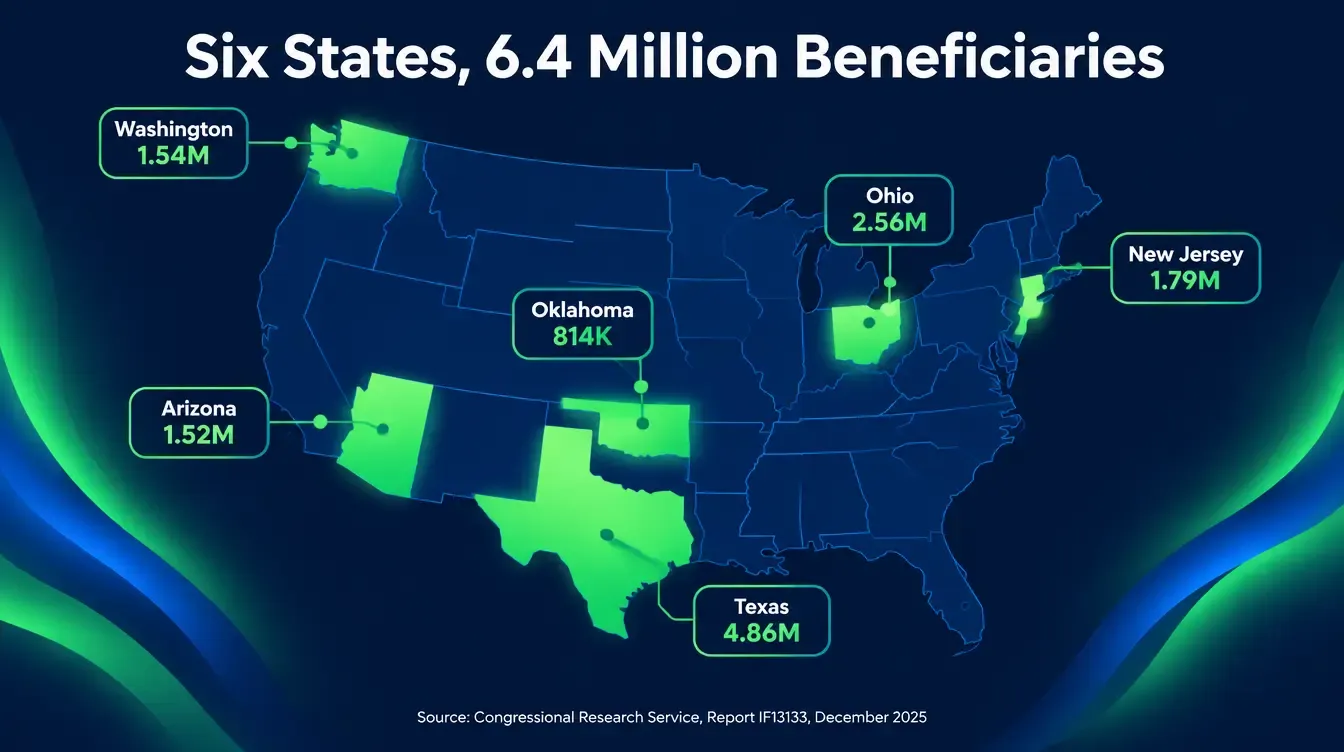
- It covers about 6.4 million Medicare beneficiaries across those six states, out of 69 million Medicare beneficiaries nationally (CRS Report IF13133, Dec. 16, 2025).
- Appeal rights are unchanged, and CMS requires a decision within three days for a standard request, two days for an expedited one (CMS, WISeR Model Frequently Asked Questions).
- Medigap doesn't touch this: it pays Medicare's cost-sharing on an already-approved claim, and WISeR operates earlier in the process, at the coverage decision itself.
- The House Appropriations Committee voted to bar funding for WISeR in its FY2027 Labor-HHS bill on June 9, 2026, while CMS's own Innovation Center director said days earlier that the model "should serve as a model" for other federal health programs (Becker's Payer Issues; HFMA). The fight over its future is live.
What the WISeR model actually is
CMS’s own framing is unusually direct: waste in health care, the agency says in its provider factsheet, “can not only harm patients but also contributes to up to 25% of health care spending in the United States” (CMS, WISeR Model Provider Factsheet). The WISeR model is CMS’s attempt to do something about a narrow slice of that, in Original Medicare specifically, by pairing six named technology companies with the Medicare Administrative Contractors (MACs) that already process claims in each region.
The structure is simple once you see it laid out. CMS picked a short list of services it considers “vulnerable to fraud, waste, and abuse,” picked six states, and assigned one technology company to each state’s MAC jurisdiction:
| State | MAC jurisdiction | Technology company | Medicare beneficiaries | Share in traditional FFS Medicare |
|---|---|---|---|---|
| Texas | JH (Novitas) | Cohere Health, Inc. | 4.86 million | 46% (2.21 million) |
| Ohio | J15 (CGS) | Innovaccer Inc. | 2.56 million | 43% (1.09 million) |
| New Jersey | JH (Novitas) | Genzeon Corporation | 1.79 million | 59% (1.05 million) |
| Washington | JF (Noridian) | Virtix Health LLC | 1.54 million | 50% (779,000) |
| Arizona | JF (Noridian) | Zyter Inc. | 1.52 million | 47% (739,000) |
| Oklahoma | JH (Novitas) | Humata Health, Inc. | 814,000 | 58% (475,000) |
The timeline is set: CMS published its request for applications June 27, 2025, applications were due July 25, 2025, the model launched January 1, 2026, and it runs through December 31, 2031 (CMS, WISeR Model Provider Factsheet; CRS Report IF13133). It’s being run under the CMS Innovation Center’s authority to test “innovative payment and service delivery models to reduce program expenditures” under Section 3021 of the Affordable Care Act, which is also the authority CMS is using here to waive the statutory limits that have historically kept prior authorization out of traditional Medicare (CRS Report IF13133).
Here’s the mechanical detail that matters most for how you talk to a client: a provider or supplier can choose to submit a prior authorization request before performing the service, or skip that and go through post-service, pre-payment review instead. Either way, “there will be no change in provider payments or providers’ appeal rights” (CMS, WISeR Model Provider Factsheet). The technology companies aren’t adjudicating in a vacuum, either — clinicians employed by the participating companies review every non-affirmation, and a human clinician reviews every denial (CMS, WISeR Model Provider Factsheet; CRS Report IF13133).
It's keyed to where the service happens, not necessarily where your client lives
CMS's factsheet says WISeR applies to "all providers in selected WISeR geographic areas serving Original Medicare beneficiaries." A client who lives in Pennsylvania but gets a procedure done at a surgery center in Dallas can be affected; a client who lives in Texas but gets the same procedure from an out-of-state provider, for that specific claim, may not be. Don't assume residence is the deciding factor when you're trying to figure out if a specific upcoming procedure is in scope.
Why this breaks a pitch you’ve probably made for years
If you’ve sold Medicare for any length of time, you’ve said some version of this sentence: “With Original Medicare, you go to any doctor who takes Medicare, no referrals, no prior authorization, no network.” That sentence has been true, in practice, for almost the entire history of the program. The Congressional Research Service calculated that in FY2023, traditional Medicare’s existing prior authorization programs — the narrow set that covers things like certain cosmetic procedures, non-emergent ambulance transport, and durable medical equipment — reviewed 3.1 million claims, representing less than 1% of the 1.2 billion total Part A and B claims filed that year (CRS Report IF13133). Prior authorization in Original Medicare has been a rounding error.
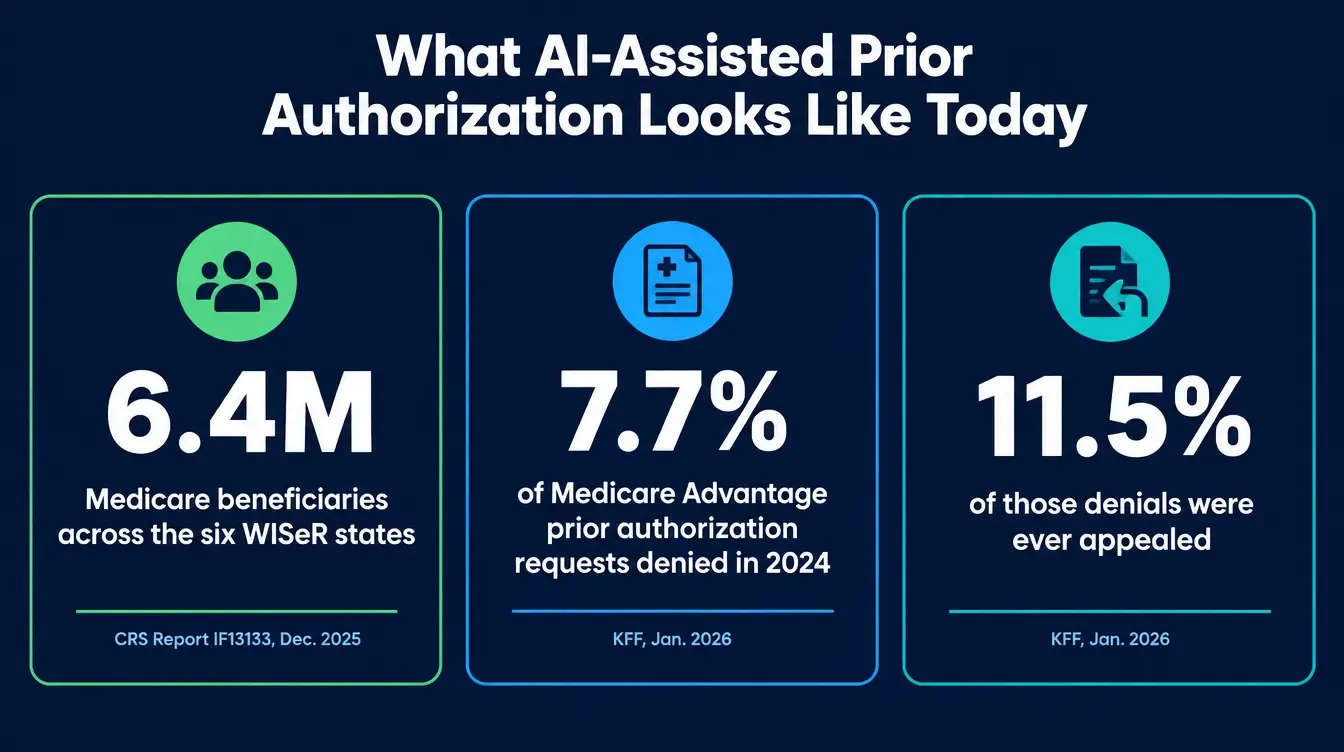
Medicare Advantage is the opposite story, and it’s worth knowing the actual scale of that contrast, because it’s the thing CMS is explicitly trying to borrow when it says WISeR “can apply artificial intelligence technologies that MA plans are already using to streamline PAs” (CRS Report IF13133). KFF’s most recent annual analysis found Medicare Advantage insurers made nearly 53 million prior authorization determinations in 2024 — about 1.7 per enrollee — of which 4.1 million, or 7.7%, were fully or partially denied. Only 11.5% of those denials were ever appealed, but when they were, 80.7% were partially or fully overturned (KFF, Medicare Advantage Insurers Made Nearly 53 Million Prior Authorization Determinations in 2024, published Jan. 28, 2026).
Prior authorization scale: traditional Medicare's existing programs vs. Medicare Advantage
Two different measurements from two sourced reports — shown together to illustrate scale, not as a single apples-to-apples rate.
Sources: Congressional Research Service Report IF13133 (Dec. 16, 2025), citing CRS's own FY2023 claims calculation; KFF, Medicare Advantage Insurers Made Nearly 53 Million Prior Authorization Determinations in 2024 (published Jan. 28, 2026).
That gap is exactly why “Original Medicare doesn’t do prior authorization” has been such a durable, true-sounding line for so long, and exactly why WISeR is a meaningful crack in it rather than a cosmetic change. It’s still a narrow pilot — fourteen service categories, six states, and CMS states explicitly that “codes in WISeR do not overlap with existing Medicare prior authorization programs” (CMS, WISeR Model Provider Factsheet) — but it’s the first time the fee-for-service side of the program has used AI-assisted review at any scale worth a client noticing.
Prior authorization in Original Medicare used to be a rounding error. WISeR doesn't make it common. It makes it exist, for the first time, in a way a client can actually run into.
Mike MooreThe services covered right now
CMS’s WISeR Model Provider Factsheet lists the service categories in scope for Performance Year 1, each tied to a specific National or Local Coverage Determination:
| Service category | Associated coverage policy |
|---|---|
| Electrical nerve stimulators | NCD 160.7 |
| Sacral nerve stimulation for urinary incontinence | NCD 230.18 |
| Phrenic nerve stimulator | NCD 160.19 |
| Vagus nerve stimulation | NCD 160.18 |
| Induced lesions of nerve tracts | NCD 160.1 |
| Epidural steroid injections for pain management | L39015, L39240, L36920 |
| Percutaneous vertebral augmentation for vertebral compression fracture | L38201, L34228, L35130 |
| Cervical fusion | L39741, L39758, L39793 |
| Arthroscopic lavage/debridement for osteoarthritic knee | NCD 150.9 |
| Hypoglossal nerve stimulation for obstructive sleep apnea | L38307, L38310, L38385 |
| Incontinence control devices | NCD 230.10 |
| Diagnosis and treatment of impotence | NCD 230.4 |
| Percutaneous image-guided lumbar decompression for spinal stenosis | NCD 150.13 |
| Skin and tissue substitutes (select jurisdictions with an active LCD) | L35041, L36690 |
That last row has its own asterisk worth knowing: the skin and tissue substitute category only applies “in selected WISeR MAC jurisdictions and states with an active LCD in place during the WISeR PYs starting on January 1, 2026, as of November 21, 2025” (CMS, WISeR Model Provider Factsheet). CMS also says plainly that these codes and the clinical documentation requirements behind them “may be subject to change,” and the authoritative, current list lives in the WISeR Provider and Supplier Operational Guide, not in any article, including this one (CMS, WISeR Model Provider Factsheet).
What it costs when nobody explains this to a client
There’s no WISeR-specific denial data yet — the model only launched in January 2026, and CMS hasn’t published outcome statistics for it. What you can source, and what’s directly relevant to how a client experiences this, is what already happens industry-wide once AI-assisted prior authorization enters a process. KFF’s 2024 Medicare Advantage figures are the closest documented precedent for how an AI-assisted review pipeline tends to behave: a 7.7% denial rate, and — this is the number that should worry you more than the denial rate itself — only 11.5% of denials ever get appealed, even though 80.7% of the appeals that do happen succeed (KFF, Medicare Advantage Insurers Made Nearly 53 Million Prior Authorization Determinations in 2024).
Read those two numbers together and the real cost comes into focus. It isn’t that AI-assisted prior authorization produces a flood of permanent denials. It’s that most people who get denied never appeal at all, even when the odds of winning are better than four in five. That gap between “denied” and “appealed” is where an agent’s explanation either closes or widens, depending on whether the client understands that a denial is a starting point, not a final answer.
What it costs you directly, as the agent, isn’t a dollar figure CMS publishes. It’s the phone call that starts with “you told me this wouldn’t happen,” and the ten or fifteen minutes you now spend explaining a federal pilot program you didn’t create and can’t control. That conversation goes a lot better when you’ve already looked up whether the client’s specific service and state puts them in scope, instead of learning about WISeR from the client.
The manual method: finding out if a client is actually affected
None of this requires anything beyond a web browser and the client’s upcoming procedure. Here’s the complete process.
Confirm the client is on Original Medicare, not Medicare Advantage
WISeR only touches Parts A and B fee-for-service claims. A client enrolled in a Medicare Advantage plan is already subject to that plan's own prior authorization rules, which are a separate, older, and much larger process — not this one.
Check where the service will actually be rendered
Look at the state where the provider's facility sits, not just where your client lives. If it's outside Arizona, New Jersey, Ohio, Oklahoma, Texas, or Washington, WISeR doesn't apply to that claim, full stop.
Match the planned procedure against the service category table above
If it's not nerve stimulation, a steroid injection for pain, cervical fusion, knee arthroscopy for osteoarthritis, hypoglossal nerve stimulation, an incontinence device, impotence treatment, lumbar decompression, or (in some jurisdictions) a skin substitute, it's not in Performance Year 1's scope.
Point the provider's office to the WISeR Provider and Supplier Operational Guide
The specific CPT and HCPCS codes, not the category names, are what actually trigger review. That operational guide, linked from CMS's WISeR model page, is the authoritative list — not this article, and not a search result.
If the service is in scope, tell the client what to expect before the appointment, not after a denial
A standard request gets a determination within three days of the reviewer receiving it; an expedited request within two (CMS, WISeR Model Frequently Asked Questions). Knowing that timeline in advance turns a surprise into a scheduling detail.
If a denial happens, explain the appeal path, don't file it yourself
"All appeals rights are preserved" (CMS, WISeR Model Frequently Asked Questions). Your role is making sure the client and the provider's office both know that a non-affirmation isn't final, and pointing them to the provider's billing office or the standard Medicare appeals process — not representing the client in that appeal.
Document that you had the conversation
A dated CRM note showing you explained WISeR before the procedure, or walked through appeal rights after a denial, is the entire defense if a client later says nobody warned them.
This is a five-minute check, not a research project
Most of your Medigap book will never touch one of these fourteen service categories in a given year. The point isn't to audit every client proactively — it's having the six-state, fourteen-category list in your head (or bookmarked) so that when a client mentions one of these specific procedures, you already know whether to flag it.
What agents should never do with this
Keep your role narrow, on purpose. You are not the provider, you are not a clinician, and you are not the client’s lawyer. If a client calls about a WISeR denial, your job is explaining what the program is, confirming the appeal path exists, and pointing them to the provider’s billing office or 1-800-MEDICARE for the actual appeal filing — not drafting the appeal letter, not interpreting the clinical rationale behind a non-affirmation, and not promising an outcome. “Results may vary,” and that’s not boilerplate here: CMS’s own data shows most appealed MA denials get overturned, but “most” isn’t “all,” and you have no way to know which bucket a specific case falls into.
Watch the compliance line, too. Walking a client through what WISeR is and how appeals work is servicing an existing policyholder, not Medicare marketing. The moment that conversation drifts into “have you thought about switching to a Medicare Advantage plan instead, since they handle this differently,” you’ve crossed into a Third Party Marketing Organization (TPMO) activity, with the Scope of Appointment and TPMO disclaimer requirements that come with it under CMS’s Medicare Communications and Marketing Guidelines. Keep the two conversations separate, even in the same phone call.
If AI tools of any kind touch this workflow, the NAIC’s AI Model Bulletin, adopted in December 2023, is the governing reference: it “reminds insurers that decisions or actions made or supported by AI must comply with all applicable insurance laws and regulations, sets forth expectations as to how insurers will govern the use of AI, and advises insurers of the type of information the Department may request during an investigation or examination” (NAIC, Insurance Topics: Artificial Intelligence). States adopt it individually and adoption is ongoing, so confirm your own state’s current status before assuming it applies the same way everywhere.
A survey of health insurers found AI-assisted prior authorization is already common, not experimental
A 2025 NAIC survey of 93 health insurance companies across 16 states, conducted November 2024 through January 2025, found 84% of respondents already use AI or machine learning in some capacity, with nearly 92% reporting AI/ML governance principles in place (NAIC, 2025 Health Insurance AI/ML Survey Results, published May 20, 2025). WISeR isn't CMS importing something exotic. It's CMS catching fee-for-service Medicare up to a practice already widespread on the private insurance side.
Where this goes next: a live fight, not a settled question
The honest answer to “is this going to spread to my state” is that nobody knows yet, and both directions have real momentum behind them right now. On one side, Abe Sutton, the director of the CMS Innovation Center, told a Paragon Health Institute webinar on September 3, 2026 that WISeR “is actually something that should serve as a model for other lines of business in how to approach authorization for services in a way that is rapid — within 72 hours — in a way that is based off of clinical evidence” (HFMA, CMMI head: WISeR should serve as model). That’s the head of the agency running the pilot saying, in public, that he wants to expand the approach.
On the other side, the House Appropriations Committee’s FY2027 Labor-HHS-Education bill, advanced at a markup on June 9, 2026, includes language that would bar CMS from using any funds “to implement the Wasteful and Inappropriate Services Reduction (WISeR) model or another model that seeks to use prior authorization practices in the traditional Medicare program” (U.S. House Committee on Appropriations, Full Committee Markup: FY2027 Labor-HHS-Education; Becker’s Payer Issues, House committee votes to block funding for WISeR prior authorization pilot). That provision still has to survive the full House, the Senate, and a presidential signature before it means anything, and appropriations riders like this one frequently don’t survive conference. The Congressional Research Service separately notes that members of Congress have sent CMS letters raising concerns, legislation has been introduced to prohibit the model outright, and litigation from providers or beneficiaries is a live possibility (CRS Report IF13133).
Nothing about this changes what’s true today: WISeR is active, in six states, for a specific list of services, right now. What it means for your clients is that this is worth a calendar reminder to check back on, not a one-time read. A rule that’s this contested in Congress and this openly championed by the agency running it is a rule that’s likely to look different a year from now, in one direction or the other.
Where the manual version breaks down at scale
Everything above — the state check, the service match, the operational guide lookup, the appeal-path explanation — is a five-minute task for one client. It becomes a different problem when you’re trying to stay current on this alongside every other CMS rule change that lands between now and AEP: the SOA timing changes, the marketing claims documentation changes, the Part D redesign, whatever shows up in the next Federal Register notice. Nobody has the bandwidth to manually re-check appropriations.house.gov, congress.gov, and CMS’s Innovation Center page every week for every program that might touch their book. That’s not a discipline problem. It’s a research-capacity problem, and it’s the same one this article’s own sourcing ran into: a CMS factsheet, a CRS report, a committee markup page, and a trade outlet, cross-checked by hand, to answer one question.
How Ambrose’s War Room and the Brain actually help with this
This is the part worth being precise about rather than oversold. Ambrose doesn’t have a dedicated “WISeR tracker” feature, and this article isn’t going to claim one exists. What’s documented and real: Ambrose’s architecture describes the Brain as “an internal service that fronts 25+ federal/healthcare data MCPs (CMS, NADAC, FDA, Federal Register, FEMA, …)” (Ambrose docs, Architecture). Sam Okafor, the War Room’s Research head, is documented with access to “brain (all .gov MCPs), marketplace-finder, agent-vault,” and the architecture notes that heads can dispatch their own depth-2 specialists via the Task tool, giving the exact example “Sam → Federal-Register specialist for rule lookups” (Ambrose docs, Executive Team).
Put plainly: asking the War Room something like “what’s the current status of the WISeR model, and has Congress actually blocked its funding yet” is precisely the kind of question that dispatch path is built to answer, by pulling the Federal Register and the Brain’s other federal sources instead of a person doing it by hand. That’s the comparison worth sitting with: the research in this article — a CMS PDF, a CRS report, a committee’s own markup page, a trade outlet’s reporting on a named official’s quote — is exactly the kind of multi-source federal lookup the War Room’s Research head is designed to run on request, in the time it takes to ask a question instead of the time it took to write this section.
| Manual step | Ambrose equivalent |
|---|---|
| Pull the CMS factsheet and FAQ PDFs for the current rules | The Brain's CMS and Federal Register sources, queried through the War Room (Ambrose docs, Architecture) |
| Check congress.gov or appropriations.house.gov for the latest legislative status | Sam Okafor dispatches to a Federal-Register specialist for exactly this kind of rule lookup (Ambrose docs, Executive Team) |
| Re-check all of it again next month, because the status could change | A scheduled Routine can re-run the same War Room question on a cron and post the answer to Slack (Ambrose docs, Routines) |
| Keep a client's denial letter out of a general AI tool | PHI Rail aliases identifiers before anything reaches a non-BAA destination (Ambrose docs, Architecture / PHI Rail) |
This is a research shortcut, not a compliance or clinical decision-maker
Nothing here automates filing an appeal, interpreting a clinical denial, or giving a client legal advice about their rights. What it shortens is the research step: finding out what a federal program currently says and whether that's changed, which is a genuinely different job from deciding what a specific client should do about a specific denial. Keep that distinction intact even once you have the seat.
What you get by joining
One Ambrose seat, including the War Room and its Research head, comes with a Tech Savvy Insurance membership: $97 a month, billed monthly, cancel anytime, founding rate locked in while the membership stays continuously active. Alongside the seat: weekly Zoom calls with open Q&A and build-with-you sessions, more than 30 hours of recorded training updated monthly, Meta Ads and AI marketing training built for health and life agents, pre-built AI templates and bot deployments, and a free annual in-person member workshop — in an explicit no-recruiting zone, so you can ask a real compliance question without getting DM’d about a downline an hour later.
Ambrose usage is separate from the $97 seat
The membership includes one Ambrose seat; usage inside Ambrose runs on its own credit ledger with spend caps, so cost stays visible instead of becoming a surprise. See the full Spokes catalog and the Executive Team page for what else the War Room covers beyond regulatory research.
Everything in this article — the state check, the service list, the operational guide, the appeal path — works whether you ever join anything or not. Go run it by hand on the next client who mentions one of these procedures, or let the War Room run the lookup for you.
Build your WISeR check before the next denial call
Bookmark the six states and fourteen service categories above, and add one line to your intake script: "is this procedure happening in Arizona, New Jersey, Ohio, Oklahoma, Texas, or Washington?" That's the whole manual system, no membership required. If you'd rather ask the War Room the same question and watch Sam Okafor's research come back in real time, one Ambrose seat comes with the Tech Savvy membership.
Join Tech Savvy — $97/monthRelated reading: our guide on Medicare drug cost lookups for the Part D side of coverage denials, our breakdown of AI compliance for insurance agents for the NAIC Model Bulletin in full, and our look at Medicare Advantage ghost networks for the network-side version of this same “what the client was told vs. what’s actually true” problem.
The close
CMS didn’t build WISeR to catch you off guard. It built it to test whether AI-assisted review can trim a slice of what it calls wasteful spending in a program that’s otherwise run prior-authorization-free for sixty years, in six states, for fourteen service categories, with appeal rights fully intact. The problem for agents is that nobody sent a memo to the field, and “Original Medicare doesn’t do prior authorization” is a sentence a lot of us have said for years without an asterisk. Add the asterisk, bookmark the state and service list, and you’ve covered the entire client-facing risk. This is the kind of live regulatory tracking we work through on a Tuesday call, watching the War Room’s Research head pull the current status instead of six browser tabs. $97 a month, cancel anytime, and nobody will pitch you a downline: https://techsavvyinsurance.com/.
Before you rely on anything in this article
Tech Savvy Insurance is a training and software community, not an insurance company, agency, or law firm, and does not provide insurance, legal, tax, or compliance advice. You are responsible for your own licensure and for complying with all applicable CMS, HIPAA, state, and carrier rules, including Medicare marketing and TPMO requirements once a conversation moves into specific plan options. AI-generated outputs may contain errors — always verify. Results may vary.
Frequently asked questions
Sources
- CMS — WISeR Model Provider Factsheet — cms.gov
- CMS — WISeR Model Frequently Asked Questions — cms.gov
- CMS — WISeR Model (Innovation Center) — cms.gov
- Congressional Research Service — Overview of the Medicare WISeR Model (IF13133, Dec. 16, 2025) — congress.gov
- KFF — Medicare Advantage Insurers Made Nearly 53 Million Prior Authorization Determinations in 2024 — kff.org
- NAIC — 2025 Health Insurance AI/ML Survey results — content.naic.org
- NAIC — Insurance Topics: Artificial Intelligence (Model Bulletin, adopted Dec. 2023) — content.naic.org
- U.S. House Committee on Appropriations — Full Committee Markup: FY2027 Labor-HHS-Education (June 9, 2026) — appropriations.house.gov
- Becker's Payer Issues — House committee votes to block funding for WISeR prior authorization pilot — beckerspayer.com
- HFMA — CMMI head: WISeR should serve as model — hfma.org
- Ambrose docs — Architecture (the Brain) — app.hiambrose.com
- Ambrose docs — Executive Team (Sam Okafor, Research head) — app.hiambrose.com
- Ambrose docs — Architecture (PHI Rail) — app.hiambrose.com
Ready to put this into practice?
Join a private community of Health & Life insurance professionals using AI, Meta Ads, and automation to grow — without draining their bank account.
Join Tech Savvy — $97/month